
First published: May 7, 2023
Last updated: September 30, 2026
Written by: Adel Galal, Founder and Editor of NextFitLife
Medical review status: This article has not been medically reviewed.
The difference between Emphysema vs COPD becomes much easier once you stop treating the words as two competing diagnoses.
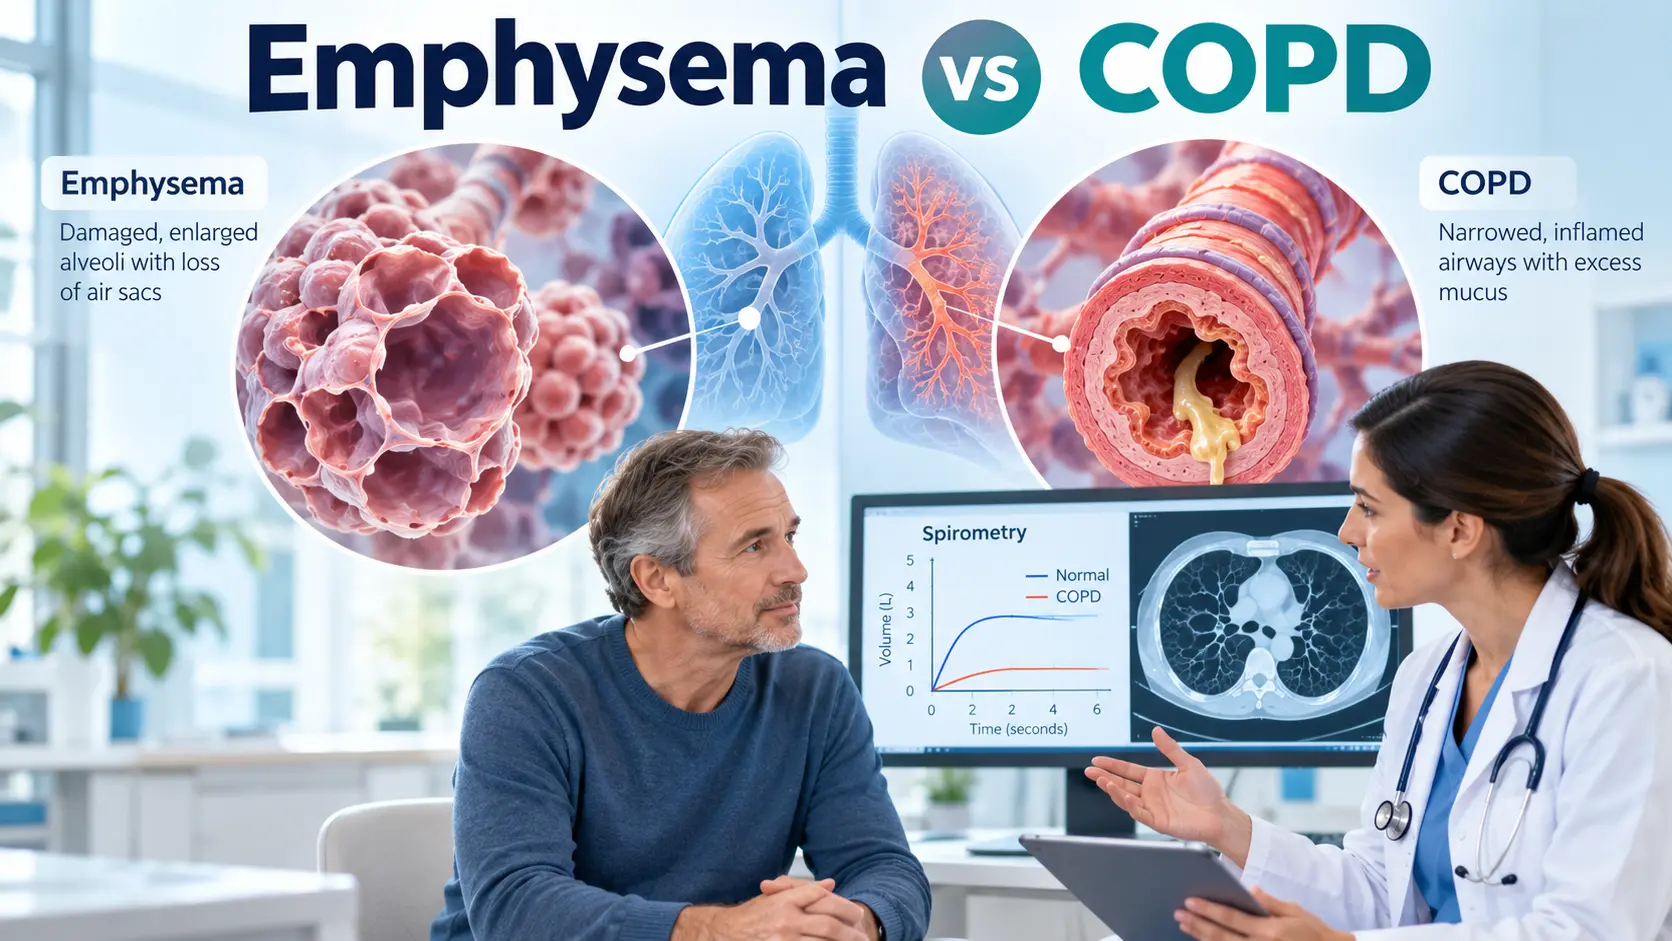
Emphysema describes damage to the tiny air sacs inside the lungs. COPD is the broader clinical condition linked with lasting breathing symptoms and persistent problems moving air through the lungs.
You can have COPD with emphysema. You can also have COPD where airway disease is more important than visible emphysema. In some people, emphysema can even appear on a CT scan before standard breathing tests confirm COPD.
Quick Answer
Emphysema means the walls of the lung alveoli have been damaged, which reduces elastic recoil and can trap air. COPD is the broader condition involving persistent respiratory symptoms and airflow obstruction. Emphysema can be one structural part of COPD, but the two terms are not interchangeable.
Get Urgent Help for Severe Breathing Symptoms
Seek urgent medical care if you have severe or rapidly worsening breathlessness, cannot speak normally because of breathing difficulty, develop blue or grey lips or skin, become confused, collapse, or have severe chest pain.
A sudden change can come from a COPD flare up, pneumonia, pneumothorax, heart problem, blood clot, or another emergency. Do not assume every new breathing problem is simply your usual COPD.
Medical notice: This content is for general educational purposes and does not replace professional medical advice, diagnosis, or treatment. Consult an appropriately qualified healthcare professional for personal medical concerns. This article explains published guidance and does not provide a personal clinical assessment. Always consult qualified medical professionals for diagnosis and treatment of any health condition.
Table of Contents
- What Emphysema Means
- What COPD Means
- 9 Critical Differences
- Can You Have Emphysema Without COPD?
- Symptoms Compared
- Causes and Risk Factors
- CT Scan vs Spirometry
- How COPD Is Diagnosed
- How Treatment Differs
- Alpha 1 Antitrypsin Deficiency
- Flare Ups and Disease Progression
- Questions to Ask Your Doctor
- When to Seek Urgent Care
- References and Sources
- Related NextFitLife Guides
- About the Author
- Frequently Asked Questions
What Does Emphysema Mean?
Your lungs contain millions of tiny air sacs called alveoli.
Healthy alveoli have thin walls and elastic tissue. They fill with air when you breathe in and help push air out when you breathe out.
They also provide a large surface where oxygen moves into the blood and carbon dioxide moves out.
In emphysema, some of the walls between these air sacs break down. Small spaces can join into larger ones, and the lungs lose some of their natural elastic recoil.
This makes it harder to empty old air.
Air can remain trapped inside the lungs, which can make the next breath feel harder.
Emphysema is therefore a structural description of lung damage.
For a full guide to testing and treatment, see our Emphysema NHS guide.
What Does COPD Mean?
COPD stands for chronic obstructive pulmonary disease.
It is the broader clinical condition.
NHS guidance describes COPD as a group of lung conditions that cause breathing problems and includes emphysema and chronic bronchitis.
Modern GOLD guidance describes COPD in terms of persistent respiratory symptoms and airflow limitation caused by airway and or alveolar abnormalities.
That means COPD can involve several problems at once:
- Narrowed small airways
- Airway inflammation
- Mucus problems
- Loss of small airways
- Damaged alveoli from emphysema
- Reduced elastic recoil
- Air trapping
Different people can have different mixtures of these changes.
Two patients with the same COPD diagnosis may therefore have very different CT scans, symptoms, mucus production, exercise limits, and treatment needs.
9 Critical Differences Between Emphysema and COPD
| Feature | Emphysema | COPD |
|---|---|---|
| 1. Meaning | Structural destruction of lung air sacs | Broader clinical condition with persistent respiratory symptoms and airflow limitation |
| 2. Main area affected | The alveoli and surrounding lung tissue | Airways, small airways, alveoli, or a mixture |
| 3. Main test | A CT scan can show emphysema directly | Spirometry is central to confirming persistent airflow obstruction |
| 4. Can imaging find it? | Yes, CT can show emphysema | Imaging can support assessment but does not replace spirometry for standard COPD diagnosis |
| 5. Mucus and cough | May occur, but structural air sac damage is the defining feature | Chronic cough and phlegm are common in many people because airway disease may be prominent |
| 6. Air trapping | Common because elastic recoil is lost | Can occur from emphysema, narrowed small airways, or both |
| 7. Can it exist alone? | Emphysema can appear on imaging without established spirometric COPD | COPD can occur with little visible emphysema when airway disease is more prominent |
| 8. Treatment focus | Treat symptoms and COPD features; selected severe cases may qualify for lung volume procedures | Smoking cessation, inhalers, rehabilitation, vaccination, self management, flare up prevention, and selected advanced treatment |
| 9. Reversibility | Destroyed alveolar tissue is not restored by routine treatment | COPD is not currently curable, but treatment can control symptoms and slow further decline |
Can You Have Emphysema Without COPD?
Yes, and this is where the usual one line explanation becomes too simple.
GOLD guidance notes that significant lung abnormalities such as emphysema can exist even when standard spirometry has not shown the airflow limitation used to define COPD.
NICE makes a similar practical point.
If emphysema or chronic airway disease is found unexpectedly on a chest X ray or CT scan, NICE recommends respiratory review and spirometry.
That means:
A CT finding of emphysema deserves attention, but it does not automatically equal a complete COPD diagnosis.
Your healthcare professional still needs to look at symptoms, smoking or exposure history, examination, and lung function.
Can You Have COPD Without Much Emphysema?
Yes.
Some people have COPD where small airway disease, inflammation, and mucus problems are more prominent than alveolar destruction.
This is one reason COPD is not simply another word for emphysema.
GOLD describes airflow limitation in COPD as the result of different mixtures of small airway disease and destruction of lung tissue.
The balance differs from person to person.
Do Emphysema and COPD Cause the Same Symptoms?
There is a large overlap.
Common COPD symptoms include:
- Shortness of breath
- Persistent cough
- Phlegm
- Wheezing
- Chest tightness
- Frequent chest infections
- Reduced exercise ability
- Tiredness
Emphysema may make breathlessness more noticeable
When emphysema is a major part of the disease, loss of elastic recoil and air trapping can make breathing out harder.
Physical activity may become difficult because the lungs struggle to empty efficiently before the next breath begins.
Airway disease may make cough and mucus more obvious
If chronic airway inflammation is more prominent, cough and phlegm may stand out more strongly.
These are trends, not rules.
You cannot decide how much emphysema someone has simply by listening to their cough.
What Causes Emphysema and COPD?
The risk factors overlap because emphysema commonly develops as part of COPD.
Smoking
Cigarette smoking remains one of the most important causes of COPD.
Smoke damages the airways and lung tissue over time.
If you currently smoke and have COPD, stopping is one of the most useful actions you can take to reduce further smoking related damage.
For a deeper explanation, see our Smoking and Lung Health guide.
Workplace Exposure
Long term exposure to dust, fumes, chemicals, and other airborne irritants can contribute to COPD.
Work history therefore matters during diagnosis.
Air Pollution
Long term exposure to polluted air can add to lung injury, although individual risk depends on the type and amount of exposure.
Alpha 1 Antitrypsin Deficiency
Alpha 1 antitrypsin deficiency is an inherited condition that can lead to emphysema, sometimes at a younger age than expected.
Testing becomes especially worth discussing when emphysema or COPD appears early, smoking exposure has been limited, or there is a relevant family history.
Which Test Shows Emphysema?
A chest CT scan is much better at showing emphysema than a basic breathing test.
CT can show damaged and enlarged air spaces and can help describe where emphysema is located.
A chest X ray may suggest emphysema in more advanced disease, but it is less detailed.
Imaging does not tell the whole story about how well you breathe.
Which Test Shows COPD?
Spirometry is central to confirming COPD.
The test measures how much air you can blow out and how quickly you can blow it out.
NICE recommends post bronchodilator spirometry to confirm COPD.
That means the breathing test is repeated after medicine that opens the airways so the clinician can assess persistent obstruction more accurately.
In March 2026, GOLD and the Global Lung Function Initiative again stressed that spirometry is essential for confirming COPD.
For more detail on lung function testing, see How to Check Lung Health.
Why Can the CT and Spirometry Tell Different Stories?
Because they measure different things.
| Test | Main Question |
|---|---|
| CT scan | What does the structure of the lung look like? |
| Spirometry | How well can air move through the lungs? |
You can therefore have visible emphysema with relatively preserved airflow.
You can also have important COPD symptoms and airflow obstruction when emphysema is not the dominant CT feature.
Neither test should be interpreted without the rest of the clinical picture.
How Is COPD Diagnosed?
A clinician usually combines several pieces of information.
Symptoms
Persistent breathlessness, cough, phlegm, wheezing, and repeated chest infections can raise suspicion.
Exposure History
Smoking, secondhand smoke, work related dust or fumes, pollution, and family history all matter.
Spirometry
This confirms persistent airflow limitation when COPD is suspected.
Imaging
Chest X ray and CT can help show emphysema and identify other problems.
Additional Tests
Depending on your situation, clinicians may use:
- Full lung function testing
- Gas transfer testing
- Blood tests
- Oxygen measurements
- ECG
- Alpha 1 antitrypsin testing
Is Treatment Different for Emphysema and COPD?
Much of the treatment overlaps because emphysema is commonly managed within COPD care.
The details depend on symptoms, flare ups, oxygen levels, lung function, CT findings, other medical conditions, and how you respond to treatment.
Stop Smoking
If you smoke, stopping is the most important step for slowing further smoking related lung damage.
Destroyed emphysema tissue does not grow back, but stopping smoking can help protect the lung function you still have.
Bronchodilator Inhalers
A bronchodilator relaxes muscles around the airways and can make breathing easier.
Short acting or long acting inhalers may be used depending on symptoms.
Combination Inhalers
Some people need combinations of long acting airway medicines.
Inhaled steroids are added for selected COPD patients based on clinical features and flare up history. They are not automatically required simply because a CT scan shows emphysema.
Pulmonary Rehabilitation
Pulmonary rehabilitation combines exercise, education, symptom management, and practical support.
It does not rebuild damaged alveoli.
It can help people function better with the lung capacity they still have.
Vaccination and Self Management
The 2026 NICE COPD checklist highlights influenza and pneumococcal vaccination, a personalised self management plan, management of other health conditions, and regular checks of inhaler technique.
Oxygen
Long term oxygen is used for selected people whose blood oxygen remains too low.
Breathlessness alone does not mean home oxygen is needed.
Lung Volume Reduction
Lung volume reduction is more specific to selected people with severe emphysema.
Removing or reducing the effect of badly damaged areas can sometimes allow healthier lung tissue and breathing muscles to work more effectively.
Options can include surgery or bronchoscopic procedures in carefully selected patients.
Lung Transplant
A small number of people with advanced COPD may be considered for lung transplantation after specialist assessment.
Does Emphysema Always Mean Severe COPD?
No.
The amount of emphysema seen on CT is only one part of the picture.
Doctors also consider:
- Breathlessness
- Exercise capacity
- Spirometry
- Gas transfer
- Oxygen level
- History of flare ups
- Other medical conditions
- Body weight and muscle strength
A CT report alone cannot tell you exactly how limited your daily life will be.
Does COPD Always Get Worse?
COPD is a long term condition, but the rate of change differs greatly between people.
Treatment cannot erase established emphysema, but it can reduce symptoms and help prevent avoidable decline.
Stopping smoking, taking prescribed medicines correctly, staying active, attending pulmonary rehabilitation when appropriate, preventing infections, and treating flare ups promptly all matter.
What Is a COPD Exacerbation?
A COPD exacerbation, often called a flare up, means your normal symptoms become noticeably worse.
You may experience:
- More breathlessness
- More coughing
- More wheezing
- More phlegm
- Changes in phlegm colour or thickness
- A clear drop in activity
- Symptoms of infection
If you have a written COPD action plan, follow it.
Do not use another person's antibiotics or steroid tablets.
Does Chronic Bronchitis Mean the Same Thing as COPD?
No.
Chronic bronchitis describes long term airway inflammation and mucus production.
It has historically been grouped with emphysema under COPD, and the NHS still uses both terms when explaining the condition to patients.
Modern COPD definitions focus more on persistent symptoms, airflow limitation, and underlying airway or alveolar abnormalities.
This is another reason simple labels can become confusing.
What About Subcutaneous Emphysema?
This is a completely different use of the word “emphysema.”
Subcutaneous emphysema means air has escaped into tissue beneath the skin. It does not mean damaged lung alveoli.
If that is the condition you are researching, read our Subcutaneous Emphysema guide.
Questions to Ask After an Emphysema or COPD Diagnosis
- Has my COPD diagnosis been confirmed with spirometry?
- Does my CT scan show emphysema?
- How much of my problem comes from airway disease versus emphysema?
- Should I have full lung function testing?
- Should I be tested for alpha 1 antitrypsin deficiency?
- Am I using my inhaler correctly?
- Would pulmonary rehabilitation help me?
- Do I need an updated COPD action plan?
- What should I do during a flare up?
- Are my recommended vaccines up to date?
- Could I ever qualify for lung volume reduction?
When Should You Seek Urgent Medical Help?
Get urgent medical advice if your breathing becomes clearly worse than usual and your normal treatment does not help.
Seek emergency care when:
- You are severely short of breath
- You are gasping
- You cannot speak normally because of breathlessness
- Your lips or skin become blue, grey, or very pale
- You become confused
- You faint or collapse
- You develop severe chest pain
- You cough up a significant amount of blood
A sudden major breathing change should not automatically be blamed on COPD. Pneumonia, pneumothorax, pulmonary embolism, heart problems, and other conditions can produce similar symptoms.
Conclusion
The most useful way to understand Emphysema vs COPD is to remember that they describe different parts of the lung problem.
Emphysema describes structural damage to the alveoli. COPD describes the broader clinical condition involving persistent symptoms and airflow limitation caused by airway and or alveolar abnormalities.
If a CT scan says “emphysema,” your next step is not to guess how severe your COPD is. Ask whether you need spirometry, full lung function testing, or respiratory review so the imaging can be interpreted alongside how your lungs actually work.
References and Sources
The following high authority sources support the definitions, diagnosis, spirometry, treatment, imaging, and COPD care information used in this guide.
- NHS.
Chronic obstructive pulmonary disease, COPD.
Explains that COPD includes emphysema and chronic bronchitis and covers symptoms, causes, progression, and care.
https://www.nhs.uk/conditions/chronic-obstructive-pulmonary-disease-copd/ - NHS.
Chronic obstructive pulmonary disease, Treatment.
Covers smoking cessation, inhalers, pulmonary rehabilitation, oxygen, ventilation, and advanced treatment.
https://www.nhs.uk/conditions/chronic-obstructive-pulmonary-disease-copd/treatment/ - National Institute for Health and Care Excellence, NICE.
Chronic obstructive pulmonary disease in over 16s: diagnosis and management, NG115.
Covers post bronchodilator spirometry, incidental emphysema on CT, inhaled therapy, alpha 1 antitrypsin testing, rehabilitation, oxygen, and specialist treatment.
https://www.nice.org.uk/guidance/ng115/chapter/recommendations - Global Initiative for Chronic Obstructive Lung Disease, GOLD.
Digital GOLD Report.
Explains COPD as persistent respiratory symptoms and airflow limitation caused by airway and or alveolar abnormalities and notes that emphysema can exist without airflow limitation.
https://goldcopd.org/digital-gold-report/ - National Heart, Lung, and Blood Institute, National Institutes of Health.
COPD Diagnosis.
Covers spirometry, symptoms, exposure history, CT imaging, other lung function tests, and alpha 1 antitrypsin deficiency.
https://www.nhlbi.nih.gov/health/copd/diagnosis
Related NextFitLife Guides and Lung Health Hub
- NextFitLife Lung and Respiratory Health Hub
- Emphysema NHS: Causes, Tests, and Treatment
- How to Check Lung Health
- Smoking and Lung Health
- Subcutaneous Emphysema: Causes, Symptoms, and Treatment
About the Author
Adel Galal is the founder and editor of NextFitLife. He writes health, fitness, nutrition, sleep, respiratory health, and healthy aging content using recognised medical, public health, and academic sources.
This content is for general educational purposes and does not replace professional medical advice, diagnosis, or treatment. Consult an appropriately qualified healthcare professional for personal medical concerns. This article explains published guidance and does not provide a personal clinical assessment. Always consult qualified medical professionals for diagnosis and treatment of any health condition.
Learn more about Adel, NextFitLife, and the site's editorial approach on the About Us page.
Frequently Asked Questions
Is emphysema the same as COPD?
No. Emphysema describes destruction of the lung air sacs. COPD is the broader clinical condition involving persistent respiratory symptoms and airflow limitation. Emphysema is one structural abnormality that can contribute to COPD.
Can you have emphysema without COPD?
Yes. Emphysema can appear on a CT scan even when spirometry has not shown the persistent airflow limitation used to diagnose COPD. The finding should still be reviewed with symptoms, risk factors, and lung function testing.
Can you have COPD without emphysema?
Yes. Some people have COPD where small airway narrowing, inflammation, and mucus problems are more prominent than emphysema.
Which is worse, emphysema or COPD?
The terms cannot be ranked that way. Severity depends on symptoms, lung function, oxygen level, exercise ability, flare ups, CT findings, and other medical conditions rather than the label alone.
Does emphysema show up on spirometry?
Spirometry measures airflow rather than directly showing damaged alveoli. Emphysema itself is better seen on CT, while spirometry helps determine whether persistent airflow obstruction consistent with COPD is present.
Does COPD show on a CT scan?
A CT scan can show structural features associated with COPD, such as emphysema and airway changes. COPD diagnosis still requires the full clinical picture and appropriate lung function testing.
Can emphysema be reversed?
Established destruction of alveolar tissue is not currently reversed by routine treatment. Smoking cessation and COPD treatment can help protect remaining lung function, reduce symptoms, and improve daily function.
Does everyone with emphysema need an inhaler?
No. Treatment depends on symptoms, spirometry, flare ups, other clinical features, and the presence of COPD. An emphysema finding on CT alone does not determine which inhaler someone should use.
Does everyone with COPD need oxygen?
No. Long term oxygen is used for selected people whose blood oxygen remains too low and who meet clinical assessment criteria.
What is the difference between chronic bronchitis and emphysema?
Emphysema describes damage to lung air sacs. Chronic bronchitis describes long term airway inflammation and mucus production. Both can occur within the broader COPD picture.
What is the main test for COPD?
Spirometry is the main lung function test used to confirm COPD. NICE recommends post bronchodilator spirometry when confirming the diagnosis.

Health & wellness writer with 30+ years of experience in nutrition, fitness, and healthy aging. Founder of NextFitLife.com — evidence-based health guidance.

